


A frenectomy is a minor surgical procedure that removes a frenum, also called a frenulum. A frenum is a small fold of tissue that connects parts of the mouth, such as the tongue to the floor of the mouth or the lip to the gums.
The procedure may be considered when a restrictive or unusually positioned frenum interferes with tongue movement, feeding, speech, gum health or dental treatment. However, the appearance of a frenum alone is not enough to determine whether surgery is needed, especially in infants and children.
Recovery is usually managed with pain relief, good oral hygiene and appropriate follow-up care. Although complications are uncommon, bleeding, infection, scarring, reattachment and changes in tongue sensation or movement can occur.
What is it for?
A frenectomy is performed to reduce problems caused by a frenum that restricts normal movement or pulls on nearby tissues.
Depending on the location of the frenum, the procedure may help to:
-
Improve tongue mobility when tongue-tie causes a clear functional problem
-
Support feeding in some infants with tongue-tie and persistent breastfeeding difficulties
-
Reduce pain experienced during breastfeeding in some cases
-
Address certain speech problems associated with restricted tongue movement
-
Reduce pulling on the gums that contributes to gum recession or inflammation
-
Support orthodontic treatment for a persistent gap between the upper front teeth
-
Prevent a restrictive frenum from interfering with dentures or other dental treatment
Not every prominent or tight-looking frenum needs treatment. The decision should be based on symptoms and function rather than appearance alone.
Frenectomy for tongue-tie
Tongue-tie, medically known as ankyloglossia, occurs when the lingual frenum restricts tongue movement. In infants, possible signs include a shallow latch, long feeding times, milk leaking from the mouth, clicking during feeding, poor weight gain and nipple pain during breastfeeding.
A frenectomy may improve breastfeeding in some infants with a confirmed restriction, particularly when it is combined with support from qualified feeding or lactation professionals. However, feeding problems often have several possible causes, and not all infants with tongue-tie require surgery. Evidence about long-term breastfeeding benefits remains limited.
In older children, tongue-tie may be associated with difficulty producing certain speech sounds. An evaluation by a speech-language pathologist may be recommended before surgery because many people with tongue-tie have no significant speech problems or learn to compensate without an operation.
Frenectomy for lip and gum problems
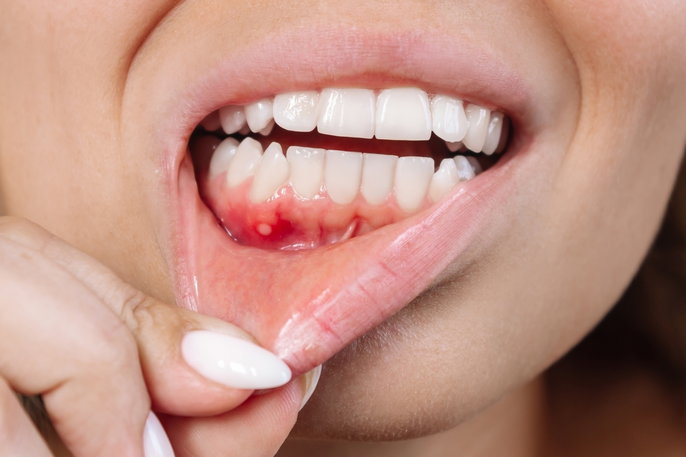
A labial frenectomy treats a frenum connecting the upper or lower lip to the gums. Surgery may be considered when this tissue pulls on the gums, contributes to gum recession or interferes with dental or orthodontic care.
An upper lip frenum may also be associated with a gap between the two upper front teeth, called a midline diastema. Many gaps in younger children close naturally as permanent teeth erupt, so frenectomy is generally delayed until the dental development and orthodontic plan have been evaluated. Performing the procedure too early may cause scarring and increase the risk of the space reopening.
Types of frenectomy
Frenectomy procedures can be classified by the frenum being treated and by the surgical method used.
1. Lingual frenectomy
A lingual frenectomy removes restrictive tissue beneath the tongue. It may be performed for tongue-tie when the restriction causes a confirmed problem with feeding, tongue movement or, in selected cases, speech.
2. Labial frenectomy
A labial frenectomy removes or repositions a frenum connecting the lip to the gums. The upper labial frenum is located between the upper front teeth, while the lower labial frenum connects the lower lip to the lower gums.
3. Buccal frenectomy
A buccal frenectomy treats a frenum connecting the inside of the cheek to the gums. Surgery is less common and is generally considered only when the tissue causes a clear functional, periodontal or dental problem.
Frenectomy, frenotomy and frenuloplasty
Although these terms are sometimes used interchangeably, they describe different procedures:
-
Frenectomy: complete removal of the frenum, including its deeper attachment
-
Frenotomy: a simple cut or division that releases the frenum
-
Frenuloplasty: a more extensive procedure that releases and rearranges the tissue, usually with sutures
The most suitable procedure depends on the patient’s age, anatomy, symptoms and treatment goals.
How the procedure is performed
The exact steps depend on the patient’s age, the location of the frenum and the technique selected:
1. Frenectomy in infants
For infants with tongue-tie, a simpler release is often performed instead of complete tissue removal. The procedure must take place in an appropriate clinical setting with professionals who are trained to manage bleeding, airway problems and other age-specific complications.
Age-appropriate pain management should be provided because both traditional and laser procedures can cause pain.
2. Frenectomy for a lip frenum
For a labial frenectomy, local anesthesia is usually placed around the treatment area. The clinician separates the abnormal tissue attachment and may remove or reposition it.
Modified surgical methods may be used when the frenum extends into the tissue between the front teeth. These techniques are designed to preserve the gum tissue between the teeth and reduce visible scarring, although the available evidence for some modified methods is based on small studies or individual cases.
Scalpel, scissors, laser and electrosurgery
A frenum can be treated using scissors, a surgical blade, a laser or electrosurgery. Traditional surgery may require sutures, while some laser and electrosurgical procedures can control bleeding without sutures.
Laser and electrosurgery may provide shorter operating times, improved bleeding control and less postoperative discomfort in some cases. However, these methods require specific training, suitable safety measures and careful patient management. No single technique is appropriate for every patient.
Recovery and aftercare
Some pain, tenderness and mild swelling can occur after a frenectomy. Pain relief should be used according to the healthcare professional’s instructions.
For older children and adults, aftercare may include:
-
Eating soft foods during the early recovery period
-
Maintaining regular oral hygiene without traumatizing the wound
-
Taking recommended pain medicine when needed
-
Attending follow-up appointments
-
Having sutures removed when non-dissolving stitches are used
Routine antibiotics and surgical dressings are not generally needed after an uncomplicated procedure.
Feeding after an infant tongue-tie procedure
Infants treated because of breastfeeding difficulty should receive continued feeding or lactation support after surgery. The frenum release may improve movement, but the infant and breastfeeding parent may still need help developing an effective latch and feeding pattern.
Skin-to-skin contact, breastfeeding and expressed breast milk may also be used as non-medication comfort measures when clinically appropriate.
Oral exercises and wound stretching
Postoperative stretching is sometimes recommended to prevent the wound from reattaching. However, professional guidance is not consistent.
The Australian consensus statement advises against stretching a surgical wound because evidence supporting the practice is lacking and stretching may prolong healing or increase scarring and infection. The American Academy of Pediatric Dentistry also notes that evidence is insufficient to support a standard stretching or massage routine, although some small studies have reported possible functional benefits from oral exercises.
Exercises should therefore only be performed when specifically recommended by the treating professional after considering the procedure, age and individual clinical needs.
Possible risks and complications
Frenectomy is generally a minor procedure, but complications can occur during surgery or recovery.
Possible complications include:
-
Pain
-
Excessive or prolonged bleeding
-
Swelling or bruising
-
Hematoma, which is a collection of blood beneath the tissue
-
Infection
-
Scar tissue formation
-
Reattachment of the frenum
-
Incomplete release of the restrictive tissue
-
Mucus retention cyst or ranula
-
Injury to a salivary gland duct
-
Numbness, tingling or altered tongue sensation
-
Restricted or worsened tongue movement
-
Feeding difficulties or oral aversion
-
Injury to nearby nerves, blood vessels or tissues
-
Airway problems, particularly in infants
Serious complications are uncommon but can be dangerous, especially in newborns. The procedure should therefore be completed by an appropriately trained professional in a setting equipped to manage bleeding, breathing problems and other emergencies.
Frenectomy also does not guarantee that the original feeding, speech, dental or functional problem will improve. Symptoms may continue when other contributing conditions are present